

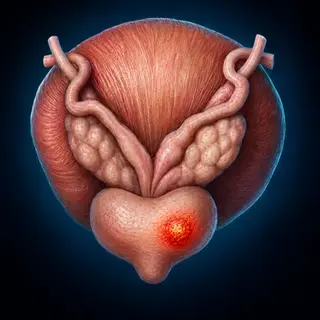
Prostate cancer is a malignant tumor that develops from cells of the prostate gland. Some tumors grow slowly over many years, while others progress faster and can spread beyond the prostate — to the lymph nodes, bones, or other organs.
For this reason, a diagnosis is never just about whether cancer is present. The tumor's grade and extent, the patient's age, general health, and treatment priorities must all be considered together.
Last medical review: 2026
Symptoms of prostate cancer
Early, prostate-confined cancer is often asymptomatic, which is why it cannot be reliably excluded on symptoms alone. As disease becomes more advanced, symptoms may include a weak urinary stream, frequent urination, blood in the urine or semen, painful urination, new erectile difficulty, or, in advanced disease, pelvic or bone pain and unexplained weight loss. Most of these symptoms are also seen in benign prostatic enlargement or infection, so their presence alone does not mean cancer.
Risk factors
Risk increases with age, and having a father or brother with prostate cancer raises risk further. Certain inherited gene changes — particularly BRCA2 — are associated with earlier or more aggressive disease, and risk varies by ethnic background. A family history of early-onset prostate cancer, several affected relatives, or a cluster of breast, ovarian, or pancreatic cancer in the family warrants closer evaluation for hereditary risk.
When should evaluation begin?
PSA testing is not a screening test that should be applied uniformly to every man at a fixed age. The decision is individualized based on age, family history, genetic risk, general health, and personal preference — typically from around age 50 for average risk, and from age 40–45 for men with a first-degree relative with prostate cancer, African ancestry, or a known BRCA2 mutation.
Does an elevated PSA mean prostate cancer?
No. PSA is prostate-specific but not cancer-specific — it can also rise with benign prostatic enlargement, prostatitis, urinary infection, retention, or certain urologic procedures. PSA is interpreted together with age, prostate volume, its change over time, digital rectal examination, family history, and multiparametric prostate MRI findings. A single PSA result does not, by itself, establish a diagnosis of prostate cancer.
How is prostate cancer diagnosed?
Diagnosis combines medical history and risk assessment, PSA testing, digital rectal examination, multiparametric prostate MRI, and prostate biopsy. MRI is scored using the PI-RADS system (1–5), which reflects how suspicious an identified area is for clinically significant cancer; higher scores generally increase the likelihood that a targeted biopsy is recommended, though the decision is based on overall risk, not PI-RADS alone. The MRI fusion biopsy technique merges MRI images with real-time ultrasound to sample suspicious areas precisely, often alongside systematic sampling of the rest of the gland.
Tissue is examined by a pathologist, who assigns a Gleason score and corresponding ISUP grade group (1–5) — a key indicator of tumor aggressiveness that helps guide treatment.
How is the stage determined?
Staging establishes whether cancer is confined to the prostate, has extended locally, or has spread to lymph nodes or distant sites, using PSA, biopsy findings, MRI, and, when indicated, additional imaging. PSMA PET/CT is not required in every patient — it is generally reserved for unfavorable intermediate-risk, high-risk, or locally advanced disease, where it helps assess for lymph node or distant spread.
Treatment options
Two patients with the same diagnosis may still be offered different treatments; the decision is individualized around PSA, Gleason/ISUP grade, MRI and biopsy extent, clinical stage and risk group, imaging results, age and life expectancy, comorbidities, urinary and sexual function, and the patient's own priorities.
Active surveillance. For low-risk, and select low-volume disease, planned monitoring with PSA, examination, MRI, and repeat biopsy allows curative treatment to be deferred while avoiding the side effects of unnecessary early treatment.
Radical prostatectomy. Complete removal of the prostate and seminal vesicles, with pelvic lymph node dissection when indicated, for patients with suitable life expectancy and localized or select locally advanced disease. Robotic radical prostatectomy can offer magnified three-dimensional visualization and precise instrument control in a confined space, and where anatomically favorable, a nerve-sparing technique may be used — but robotic access alone does not guarantee cancer control, continence, or sexual function.
Radiotherapy. A curative option for localized or locally advanced disease, delivered as external beam radiation, brachytherapy, or combinations with hormone therapy depending on risk group.
Focal therapy. In carefully selected, clearly localized disease, treatment can target only the involved area of the gland; long-term outcome evidence is not yet as robust as for radical prostatectomy or radiotherapy.
Systemic therapy. Hormone (androgen deprivation) therapy is used in node-positive or metastatic disease, often combined with radiotherapy, newer-generation androgen-pathway drugs, or chemotherapy depending on disease extent.
Follow-up after treatment
Follow-up is tailored to the treatment received. After radical prostatectomy, PSA is expected to fall to an undetectable or very low level; after radiotherapy, PSA declines more gradually since the gland is not removed. During active surveillance, PSA is combined with MRI and, when needed, repeat biopsy. If PSA rises, further imaging and salvage treatment options are considered based on the likelihood of recurrence. Follow-up addresses not only cancer control but also urinary continence, sexual function, and quality of life.
Frequently asked questions
Is an elevated PSA always cancer?
No. PSA can also rise with benign prostatic enlargement, prostatitis, infection, or recent procedures. It is interpreted together with age, prostate volume, its trend over time, examination, and MRI — not as a stand-alone diagnosis.
Does every prostate cancer patient need surgery?
No. Low-risk and select low-volume disease may be managed with active surveillance. Treatment is chosen individually based on risk group, age, general health, and the patient's priorities.
Is sexual function preserved after robotic prostatectomy?
Where anatomically favorable, a nerve-sparing technique may be used to support erectile function, but the outcome depends on the patient's baseline function, age, and cancer characteristics near the nerves — it cannot be guaranteed for every patient.
How long is recovery after robotic surgery?
Because it is minimally invasive, recovery after robotic radical prostatectomy is generally faster than after open surgery, and many patients return to routine activity within a few weeks — though this varies by individual.
Source: European Association of Urology (EAU) Guidelines on Prostate Cancer, 2026. This content is for general information only and does not replace individualized medical evaluation. Prepared and medically reviewed by Professor Cenk Acar, Urologic Oncologist.